Healthcare Procurement Consulting: What It Covers
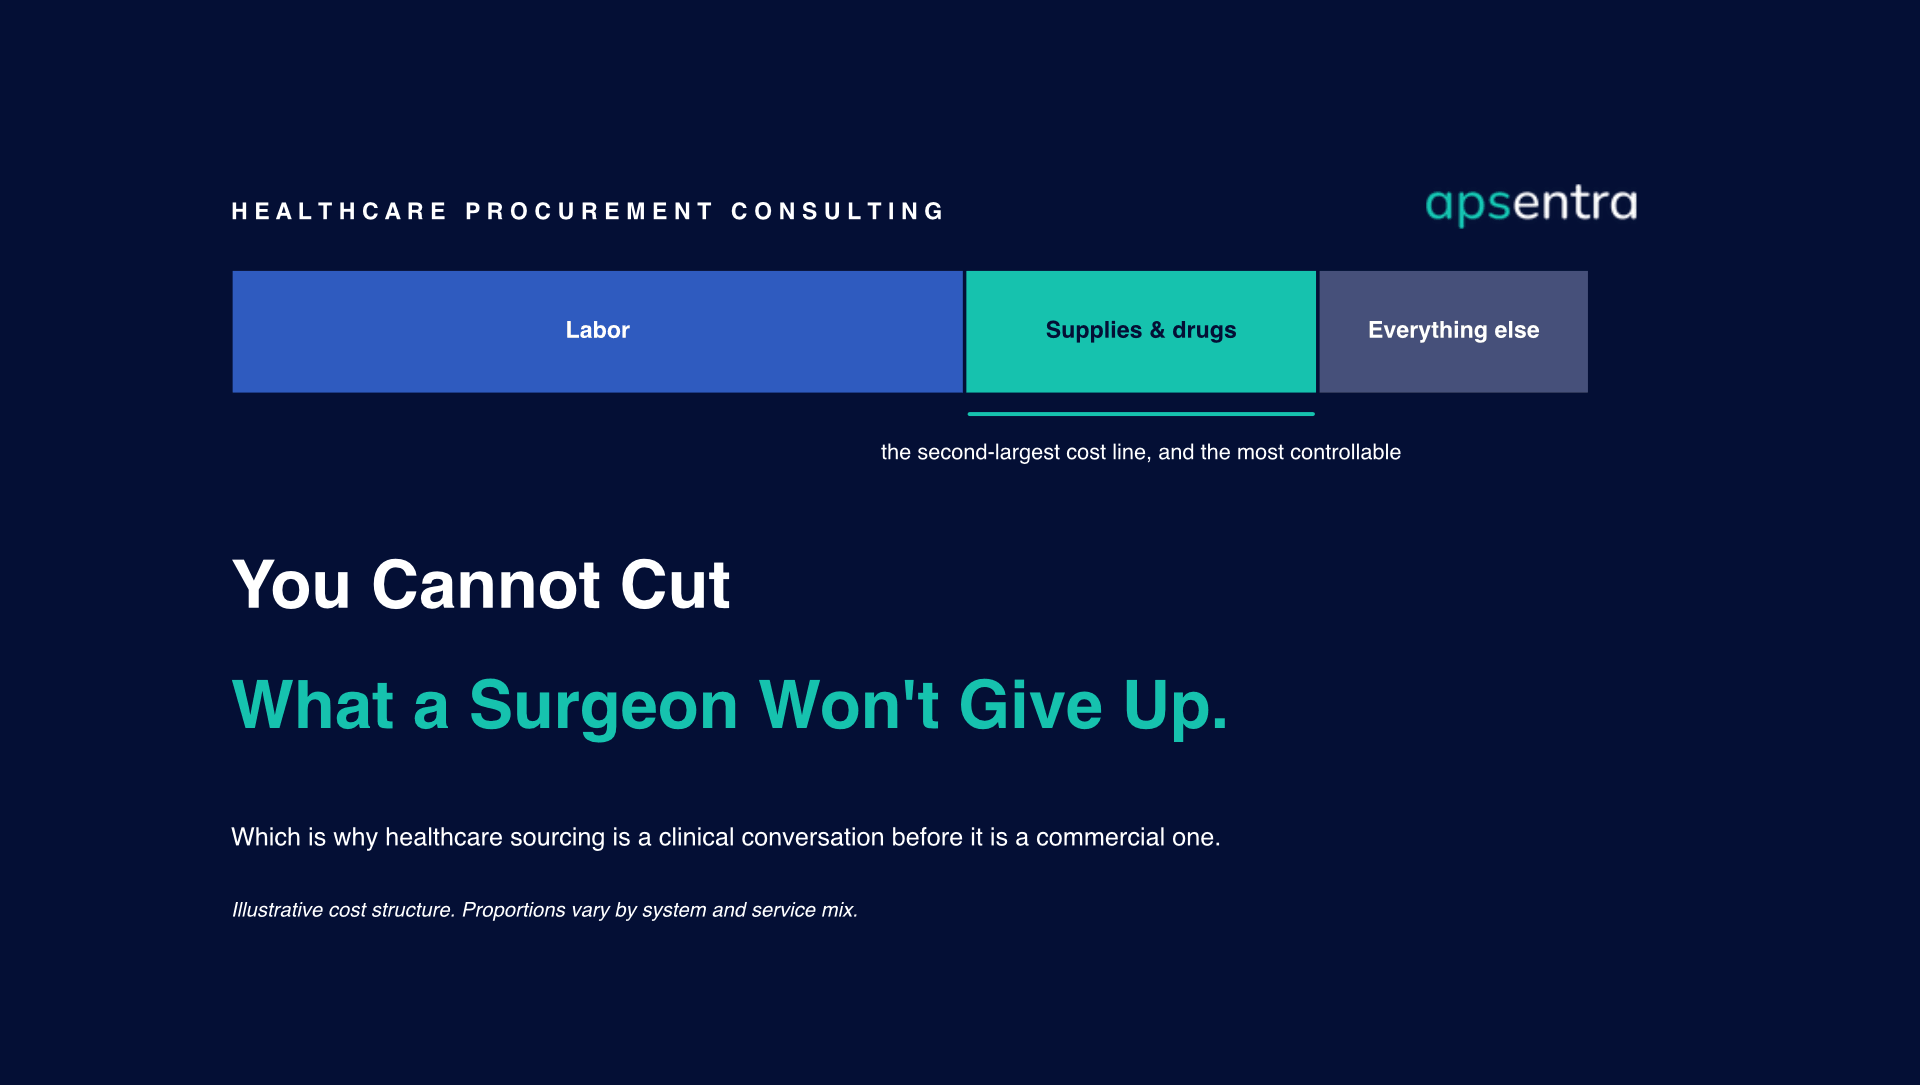
The pressure is not abstract. The American Hospital Association’s 2026 Cost of Caring report found that total hospital expenses grew 7.5 percent in 2025, more than twice the rate of growth in hospital prices, with supply expenses up 9.9 percent and drug expenses up 13.6 percent. Input costs are rising faster than reimbursement, and supplies are the line item where a decision this quarter still changes the number.
That makes procurement one of the few genuine margin levers available to a health system. It also makes it one of the hardest, because the biggest savings sit in categories where a clinician, not a buyer, decides what gets used. This guide covers what healthcare procurement consulting does, where the money actually is, and what an engagement costs.
What Healthcare Procurement Consulting Covers
Healthcare procurement consulting is sourcing and supply chain advisory for hospitals, health systems, and ambulatory providers. It covers GPO strategy and contract optimization, physician preference item sourcing, purchased services, commodity med-surg, value analysis governance, and item master and data cleanup, with savings delivered through clinical alignment rather than negotiation alone.
The defining feature is that procurement does not control the demand. A surgeon selects an implant, a cardiologist selects a device, a department head selects a service vendor. Procurement negotiates the price of a decision somebody else already made, which is a structurally weaker position than in almost any other industry.
This is why the work looks less like tendering and more like governance design. The consulting question is rarely “can we get a better price” and almost always “can we get agreement on a standard, and will it hold.” That is a procurement operating model question in clinical dress.
One clarification: the terms are used interchangeably, but they shouldn’t. This article is about buying for care delivery: hospitals and health systems purchasing supplies, devices, and services. Procurement inside pharmaceutical and device manufacturers is a different discipline with different regulations.
What a GPO Does, and What It Leaves on the Table
Almost every US hospital belongs to a group purchasing organization, and the value of that membership is real and measurable. It is also frequently misunderstood as the end of the sourcing job rather than the start of it.
A 2025 study in the Journal of Public Economics by Lin and Wang (DOI 10.1016/j.jpubeco.2025.105380) offers some of the first rigorous evidence on the question. Using a two-way fixed effects model across US hospitals, the authors find that a one-standard-deviation increase in GPO scale reduces an average hospital’s supply expenses by 2.7 percent, worth about $48 per discharge or roughly $0.72 million a year. They find no evidence that these savings come at the cost of care quality, and some of the savings are passed to patients as lower prices, though only in highly competitive hospital markets.
What the GPO does not do is govern your behavior. It negotiates access to a price. Whether your organization actually buys at that price, on that contract, at that tier, is entirely an internal matter, and it is where consulting engagements usually find most of their value.

Tier optimization

Local and custom contracting

Purchased services
Physician Preference Items: The Category That Decides the Number
Every serious healthcare sourcing program eventually arrives at the same uncomfortable place.
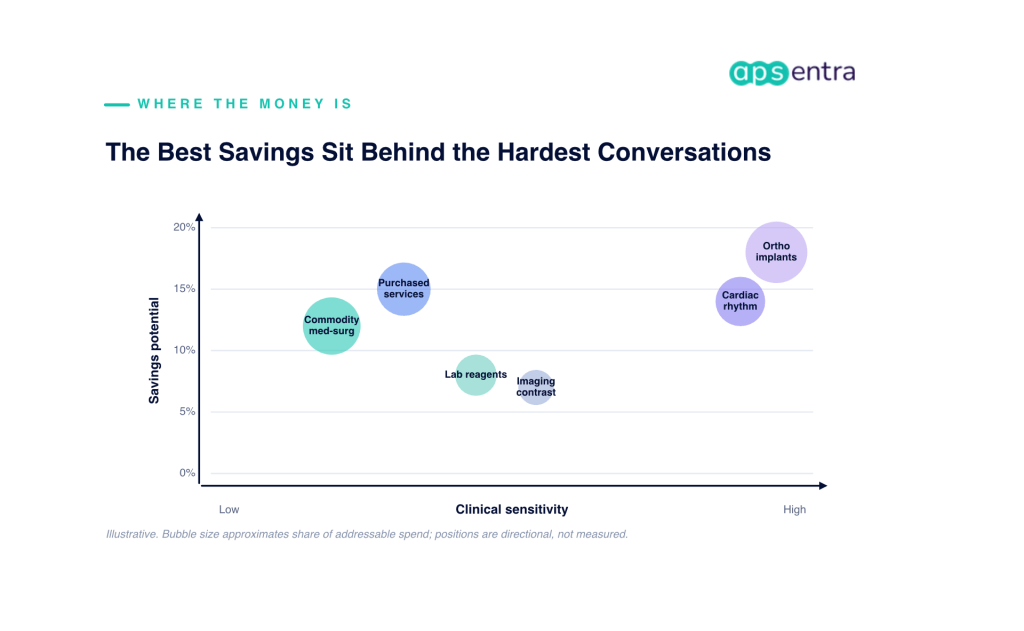
Physician preference items, principally orthopedic implants, cardiac rhythm management devices, and spine, carry the largest savings potential and the highest clinical sensitivity at the same time. The categories that are easiest to standardize are the ones with the least money in them.
This is why purely commercial approaches stall. A sourcing team that runs a competitive event on implants without surgeon participation will produce a price and no adoption. The contract will exist and the purchasing behavior will not change, which is the specific failure mode the compliance section below describes.
What works is narrower and slower. Construct a clinically acceptable set of options rather than a single winner. Share utilization and cost variation data with the physicians who generate it, by name where the culture permits and blinded where it does not. Tie the conversation to outcomes data, not just price, so it is a clinical discussion with a financial consequence rather than the reverse.
The category-strategy discipline underneath this is general, even if the stakeholder dynamic is not, and is set out in category management consulting.
Contract Compliance and Where Spend Leaks
A negotiated price only matters if it is the price on the invoice. In healthcare, the gap between those two things is unusually wide and unusually well tolerated.
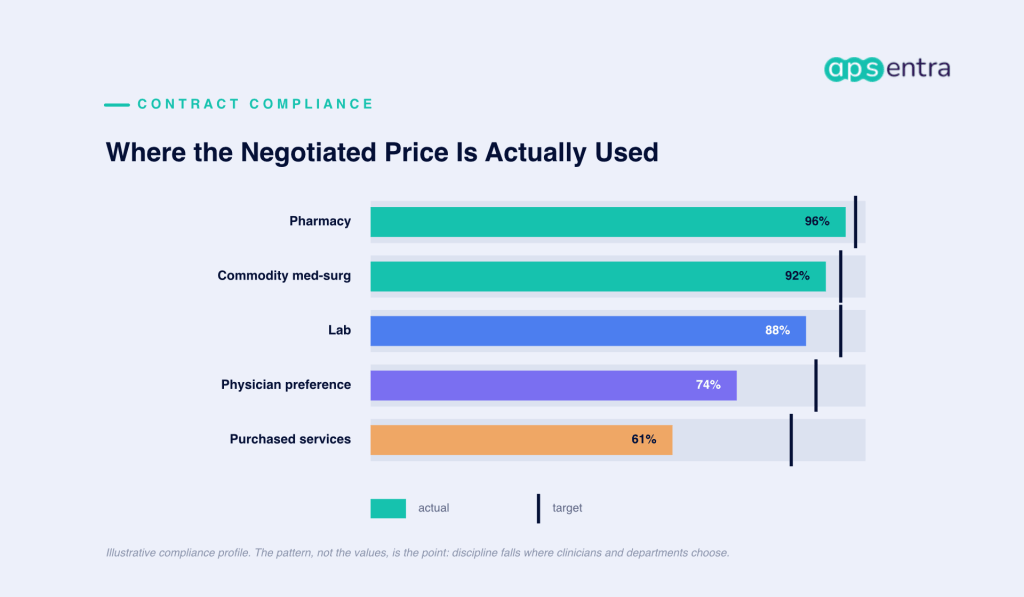
The pattern above is consistent across health systems. Compliance is high where a pharmacist or a supply chain professional makes the selection, and it falls sharply wherever a clinician or a department head makes it. That is not a discipline problem. It is a design problem: nobody built a system that makes the compliant choice the easy one.
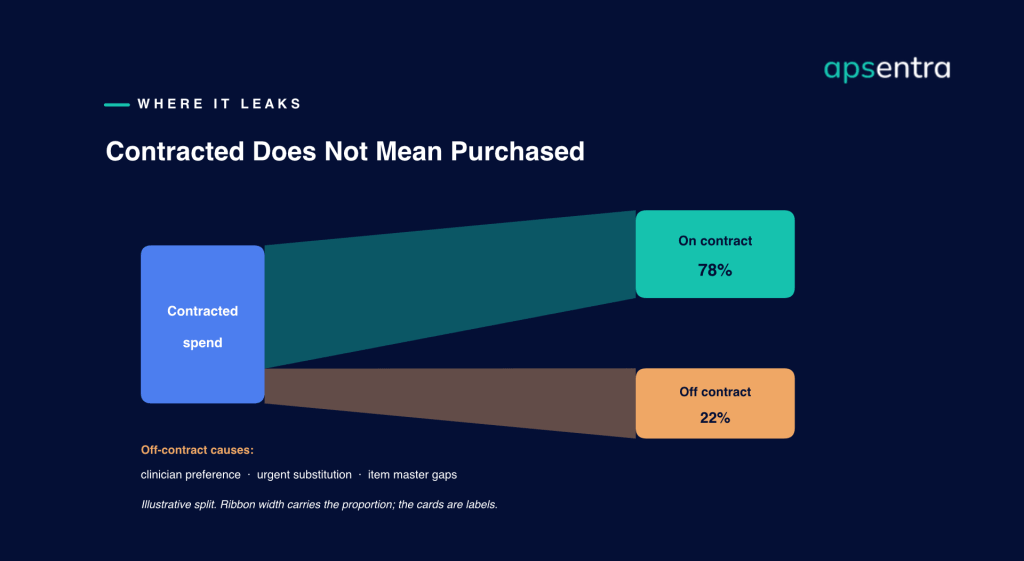
Three causes account for most off-contract purchasing, and only one of them is about preference.

Clinician preference

Urgent substitution

Item master gaps
The third cause is where consulting engagements most reliably add value, because it is pure data work that nobody internally has time to do. It is also the healthcare instance of the general leakage argument, and the controls that close it are in our procurement audit checklist.
Price Benchmarking Without Fooling Yourself
Benchmarking is the standard opening move of a healthcare sourcing engagement, and it is also the easiest place to produce a number that does not survive scrutiny.
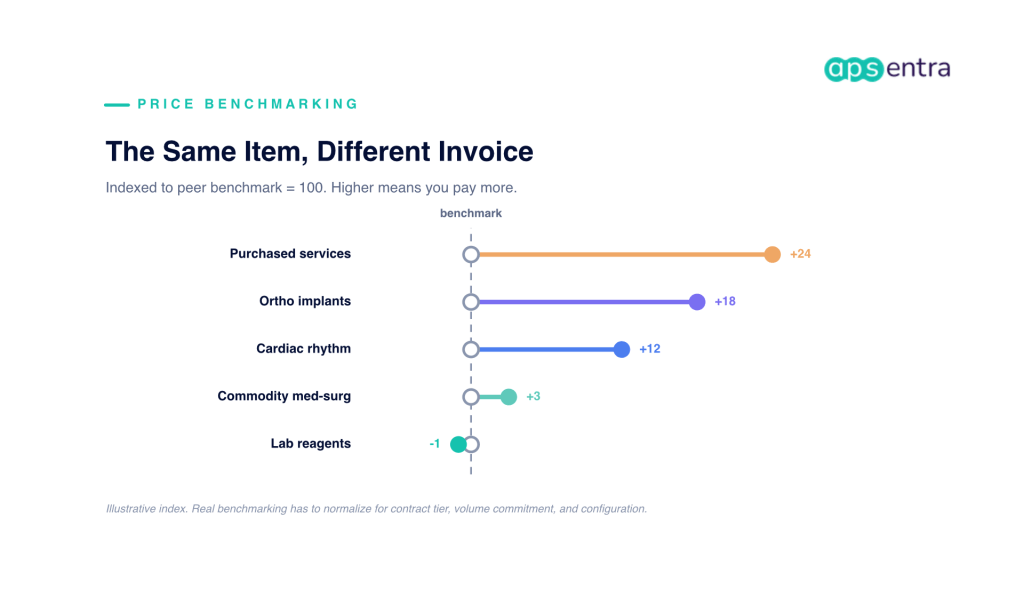
The chart shows the usual shape: the widest gaps appear in purchased services and physician preference items, the two categories with the least internal price transparency. Commodity categories cluster near the benchmark because everyone is buying the same thing on similar terms.
Three adjustments separate a defensible benchmark from a misleading one, and a proposal that skips them is worth questioning.
- Normalize the configuration. Two hospitals buying the same implant may be buying different kits, with different instrumentation, service, and consignment terms baked into the price.
- Account for tier and commitment. A peer paying less may have committed to a volume share you are not willing to commit to. That is a choice, not a failure.
- Check the peer set. Benchmarks drawn from a different case mix, region, or facility size describe a different hospital. Ask what the comparison group is before accepting the gap.
The honest framing is that a benchmark is a hypothesis about where to look, not a savings number. Treating it as the latter is how programs end up reporting savings that finance cannot find, which is the problem examined in why procurement ROI fails CFO scrutiny.
Value Analysis: The Governance That Makes It Stick
The value analysis committee is the mechanism healthcare invented to solve exactly this problem, and in most organizations it underperforms for predictable reasons.
- It meets too late. A committee that reviews products after a trial has already happened is ratifying a decision, not making one.
- It lacks a standing data view. Without current utilization, price, and outcome data in the room, the loudest clinical voice wins by default.
- It has no enforcement path. A decision that does not change what is orderable in the system is a recommendation. The next urgent case will override it.
- It is not tied to the budget. When approvals carry no financial consequence for the requesting service line, every request looks free to the requester.
A functioning value analysis process is the difference between a savings program and a savings report. Fixing it is usually less glamorous than a sourcing wave and worth considerably more over three years, because it changes what happens after the consultants leave.
The general version of that argument, and the reason it recurs in every article in this cluster, is set out in when your team needs a consultant and when it needs a better system.